You move to Boston with a carefully organized dental file. The report says tooth 46 has a crown, tooth 11 was injured years ago, and tooth 24 needs monitoring. At the new appointment, the dentist starts talking about tooth 30, tooth 8, and tooth 25. For a moment, it can sound as though the records belong to someone else.
They may be describing the same mouth in two different numbering systems. Dentistry uses more than one convention for identifying teeth, and the system common in the United States is not the one used in many other countries. The numbers are administrative shorthand. They are not a diagnosis, and they should always be confirmed against the tooth’s location, images, and clinical findings.
The United States commonly uses the Universal system
The American Dental Association describes the Universal or National Tooth Numbering System as the code set most commonly used in the United States. Permanent teeth are numbered from 1 through 32. The sequence begins at the upper right third molar, travels across the upper arch, drops to the lower left third molar, and continues across the lower arch to the lower right third molar.
That creates a continuous route around the mouth. Upper front teeth are numbers 8 and 9. The lower right first molar is number 30. Primary teeth use letters rather than the same adult numbers. A person does not need to memorize this map, but it helps to know that a single number is meaningful only within a named system.
Many countries use the FDI two-digit system
ISO 3950 provides a two-digit designation system for teeth and areas of the oral cavity. In the FDI system for permanent teeth, the first digit identifies the quadrant and the second identifies the tooth’s position from the center line. Quadrant 1 is upper right, 2 is upper left, 3 is lower left, and 4 is lower right, from the patient’s perspective.
The second digit runs from 1 at the central incisor to 8 at the third molar. Tooth 46 is therefore in quadrant 4 and is the sixth tooth from the center: the lower right first molar. In the U.S. Universal system, that same tooth is number 30. The two numbers look unrelated because the systems organize the mouth differently.
Some familiar numbers can be especially misleading
A record that says tooth 11 in FDI notation refers to the upper right central incisor. In Universal notation, tooth number 11 is the upper left canine. FDI 24 is the upper left first premolar; Universal 24 is a lower left central incisor. These are not small differences. If a number is copied without the notation system, it can point to a completely different tooth.
That is why a transfer note should ideally name the tooth in words as well as by number, especially when treatment is planned. ‘Lower right first molar, FDI 46, Universal 30′ is far clearer than ’46’ standing alone. A simple notation label can prevent confusion when records cross countries, software systems, laboratories, or referral offices.
A translated number still does not confirm the treatment
Even when the conversion is correct, the receiving dentist should compare the written record with the mouth and the images. Teeth may be missing. Wisdom teeth may never have developed or may have been removed. A tooth may have moved after orthodontic treatment. Records can contain typographical errors, reversed radiographs, outdated treatment plans, or notes written under a different convention.
The safe question is not only, ‘What does 46 equal?’ It is, ‘Which physical tooth did the earlier clinician mean, and what was found there?’ The answer may come from the tooth’s name, surface, restoration, date, radiograph, scan, photograph, and operative note. Before irreversible care, the present clinical findings must agree with the transferred information.

Implant records need more than a tooth number
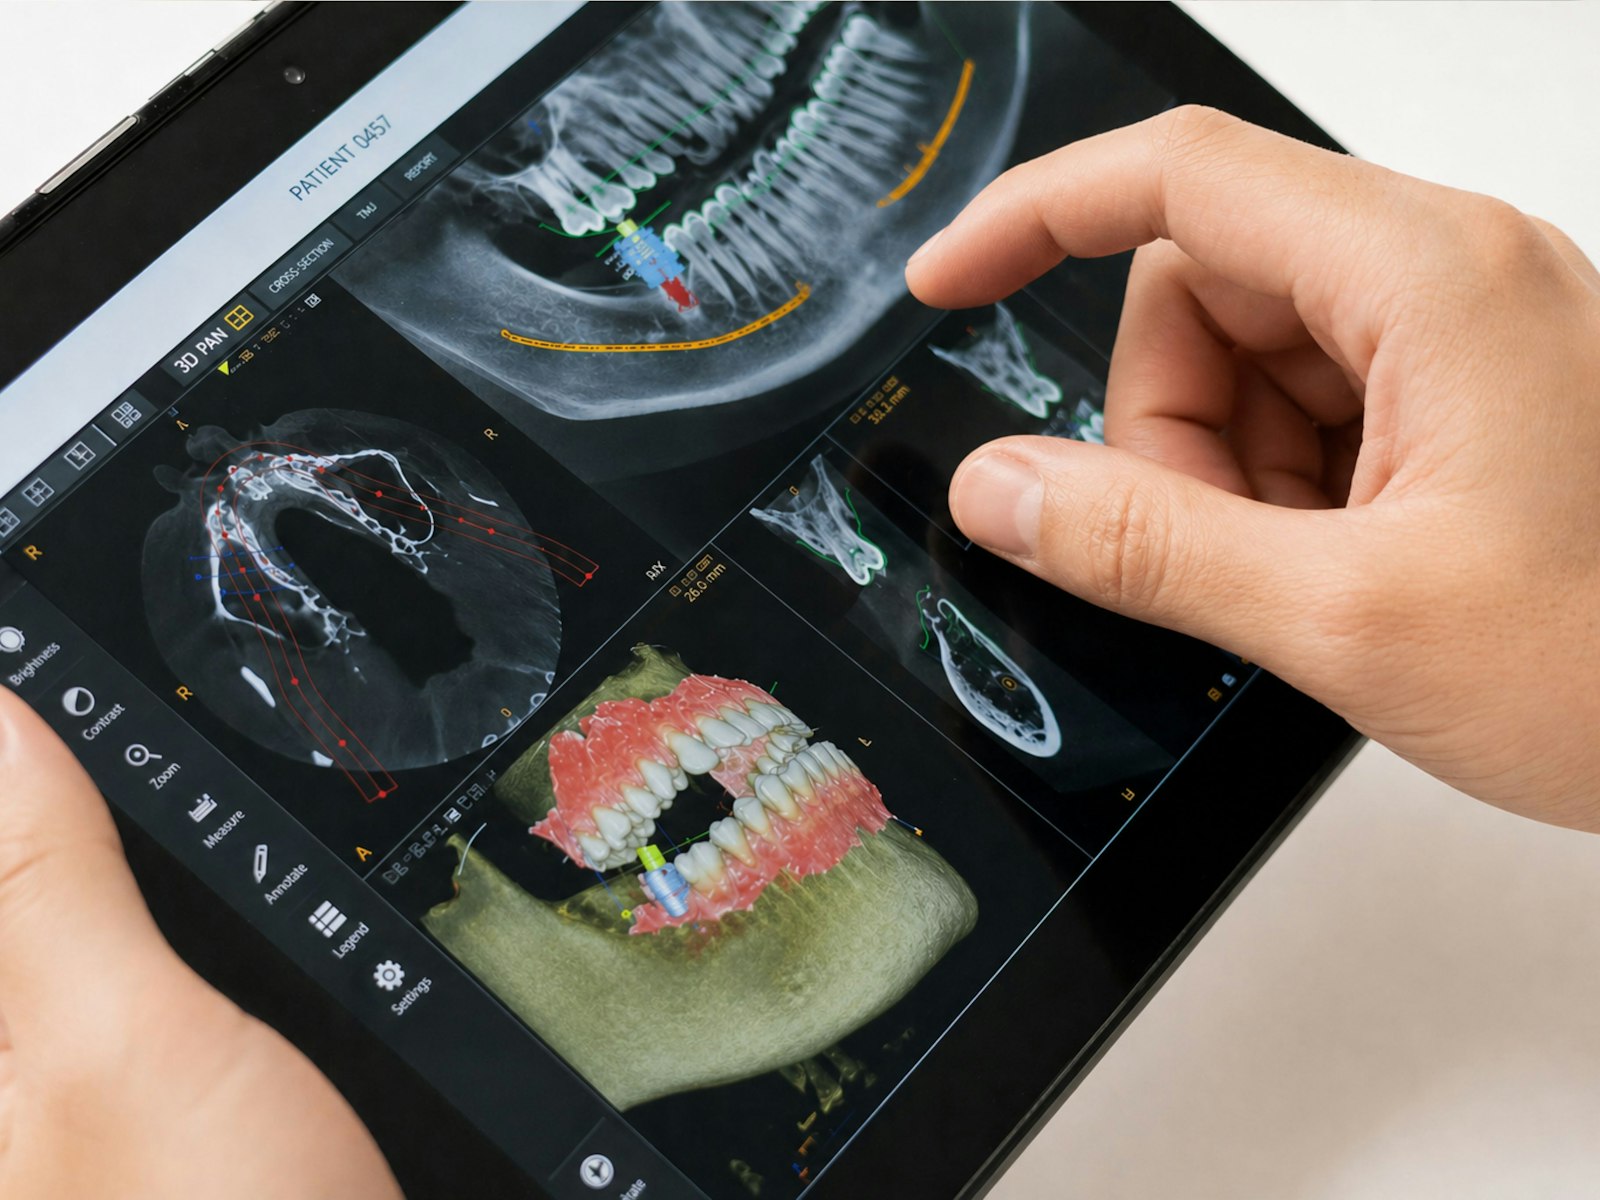
An implant may be described by the tooth position it replaces, but the number does not identify the implant system. For future maintenance or repair, useful records may include the manufacturer, implant model, diameter, length, connection type, abutment, screw, restoration design, placement date, and treating clinician. A panoramic image alone may not provide all of those details.
This becomes important when a crown loosens years later or a full-arch restoration needs service in another country. Compatible components cannot be selected from ‘implant at 46’ alone. If you are preparing to move, ask for the implant passport, product stickers, operative note, and restorative component information while the original office can still retrieve them easily.
Build a record package that can survive another move
International students, researchers, executives, and families in Boston and Cambridge may receive portions of their care in more than one country. A concise, well-labeled record set can reduce repeated investigation and make a new consultation more efficient. It does not need to be enormous. It needs to be specific.
A current written summary naming both the tooth and the numbering system
Dated X-rays or scans in their original diagnostic quality when available
Procedure dates and the reason each tooth was treated
Implant, abutment, screw, and restoration details for any implant-supported work
Materials or laboratory information for complex crowns, veneers, bridges, or full-arch restorations
If the records are not in English, a professional translation of the clinical summary may help, but preserve the original document too. Do not convert tooth numbers by globally replacing digits in a file. Label the original system and let the receiving clinician reconcile it with the images and examination.
What to say at the first Boston-area appointment
Tell the office where the records were created and which numbering system appears to have been used. Point out any uncertainty rather than trying to resolve every number yourself. If a report uses an unfamiliar abbreviation, ask the earlier office for clarification when possible. Bring a medication list and relevant medical history along with the dental records, because treatment decisions depend on more than the charted tooth.
If a tooth is painful, swollen, fractured, or acutely infected, seek care even if the records are incomplete. Documentation is valuable, but it should not delay evaluation of an urgent problem. The current dentist can begin with the clinical situation and incorporate earlier information as it becomes available.
Complex-record consultations in Belmont
Dental Restorative Group’s website lists dental implants, crowns, bridges, veneers, full-arch implant treatment, and planning for complex restorative cases. These are precisely the kinds of treatments for which clear records, implant identification, and accurate tooth designation become especially useful.
If your records were created outside the United States and the numbers no longer seem to match, do not assume the information is wrong. Bring the original records to a consultation and let the notation be translated into a current tooth-by-tooth examination. The goal is not merely to rename tooth 46 as tooth 30. It is to make sure everyone is talking about the same tooth, the same history, and the same decision before treatment proceeds.
Frequently Asked Questions
Is FDI tooth 46 the same as U.S. tooth 30?
Yes. Both designate the permanent lower right first molar, but they belong to different numbering systems.
Why does my new dentist use different tooth numbers?
The United States commonly uses the Universal system, while many other countries use the FDI two-digit system. The tooth has not changed; the notation has.
Can I convert my dental records myself?
A chart can help with basic mapping, but the dentist should confirm the physical tooth, images, and current findings. Missing teeth, earlier errors, and mixed notation can create confusion.
What implant records should I bring from another country?
Bring the manufacturer, model, diameter, length, connection, abutment and screw details, placement date, operative notes, earlier images, and restoration information when available.
Dental Restorative Group, 385 Concord Avenue, Suite 100, Belmont, MA 02478. Phone: 617-489-1470.
This article provides general educational information and does not replace an examination or individualized dental or medical advice. Diagnosis, timing, and treatment recommendations depend on the patient’s health and clinical findings.